Cortisol
Does Cortisol Cause Belly Fat?
The claim: high cortisol causes belly fat and weight gain, and a “cortisol detox” can fix it.
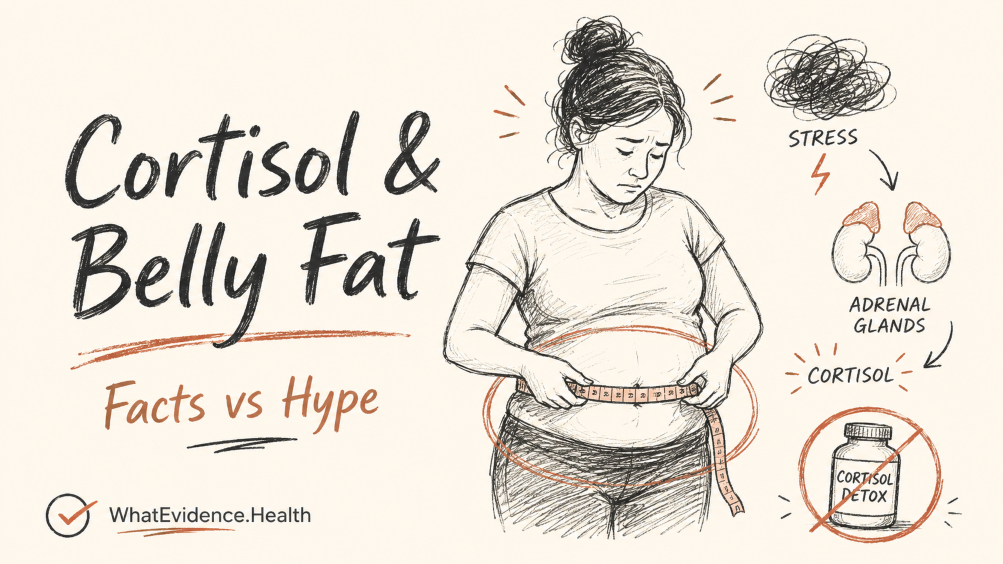
Cortisol is not a toxin. It is an essential hormone made by the adrenal glands, and it helps regulate stress responses, inflammation, blood sugar, and blood pressure.1 Severe or chronic medical cortisol excess, as in Cushing syndrome, can clearly cause central weight gain. But for most stressed adults, the link between cortisol and belly fat is real but indirect, variable, and much weaker than social media claims suggest.56
At a Glance
What is cortisol?
Cortisol is a glucocorticoid, which means a steroid hormone involved in metabolism, inflammation, and the body’s response to stress. It is made by the adrenal glands, which sit above the kidneys. It can be measured in blood, urine, or saliva.1
Cortisol is released through the HPA axis. HPA means hypothalamic–pituitary–adrenal. In simple terms, the brain signals the pituitary gland, the pituitary signals the adrenal glands, and the adrenal glands release cortisol.
Cortisol also follows a daily rhythm. In most people with a regular sleep schedule, levels rise before waking and usually peak within about 30 to 60 minutes after waking. This is called the cortisol awakening response.2
What the Evidence Says
1. Clinical high cortisol is different from being stressed
Cushing syndrome is the clearest example of harmful cortisol excess. It can happen because the body makes too much cortisol, or because a person has taken glucocorticoid medicines such as prednisone or dexamethasone for long enough to cause cortisol-like effects. The clinical pattern is not just “feeling stressed”. It is usually progressive and includes features such as central weight gain, rounded face, fat at the upper back, skin thinning, easy bruising, wide purple stretch marks, muscle weakness, high blood pressure, diabetes, and low bone density.414
Guidelines recommend testing for Cushing syndrome when people have multiple, progressive, or unusual features, especially features that are more specific for cortisol excess. Recommended first-line tests include 24-hour urinary free cortisol, late-night salivary cortisol, and the 1 mg overnight dexamethasone suppression test. Random serum cortisol is specifically not recommended as a screening test.13
2. The belly-fat claim is biologically plausible, but often exaggerated
There are plausible mechanisms. Cortisol can affect appetite, glucose metabolism, fat storage, and local cortisol activity in adipose tissue. Reviews of stress and obesity describe a two-way relationship: chronic stress may contribute to obesity risk, and obesity itself may alter stress biology.5
The problem is that real-life human studies are messy. A systematic review of obesity and HPA-axis activity found a general pattern linking abdominal fat with higher HPA-axis responsiveness, but also found inconsistent results across methods and studies.6 Hair-cortisol reviews suggest long-term cortisol exposure is more related to abdominal obesity than single blood or saliva samples, but this still does not prove that cortisol is the main cause of belly fat in an individual person.7
3. Lowering cortisol is not the same as losing belly fat
Stress management can change cortisol markers. In a 2024 systematic review and meta-analysis, stress management interventions outperformed control conditions for cortisol, with mindfulness, meditation, and relaxation among the more effective categories.8 Exercise may also help, especially mind–body practices such as yoga and qigong in adults with psychological distress.9
But this is not proof of targeted belly-fat loss. A lower cortisol value does not automatically mean fat loss, and fat loss depends on energy balance, sleep, diet, physical activity, medicines, medical conditions, and genetics. The strongest practical advice is to treat stress reduction as part of general metabolic health, not as a spot-reduction trick.
4. Ashwagandha is not a cortisol detox
Ashwagandha has more evidence than most “cortisol support” supplements, but the evidence is still limited. A 2025 systematic review and meta-analysis reported lower measured cortisol in randomized trials, while also noting uncertainty around perceived stress effects.10 Official safety sources caution that long-term safety is not known and that ashwagandha may interact with medicines, affect thyroid function, and rarely be linked with liver injury.1112
Are Results Consistent Across Studies?
Why We Rate It This Way
- Supported: pathological cortisol excess can cause central weight gain and requires medical assessment.
- Uncertain: everyday stress-related cortisol is not a reliable stand-alone explanation for belly fat in otherwise healthy adults.
- Promising: mindfulness, relaxation, yoga, qigong, and possibly ashwagandha can lower cortisol markers in some studies.
- Not supported: “cortisol detox” has no recognised clinical definition and no meaningful trial evidence.
Safety Note
Do not stop prescription steroids suddenly. Prednisone, dexamethasone, hydrocortisone, inhaled steroids, topical steroids, and steroid injections can affect the HPA axis. Stopping suddenly can be dangerous, especially after longer use.
Be cautious with ashwagandha. Official sources advise avoiding it during pregnancy and breastfeeding, and caution in people with thyroid disorders, autoimmune disease, liver disease, hormone-sensitive prostate cancer, or use of sedatives, thyroid medicines, blood pressure medicines, diabetes medicines, anticonvulsants, or immunosuppressants.1112
What This Means For You
Use cortisol as a medical clue, not a wellness villain.
- If you have Cushing-like features, ask a doctor about proper testing rather than buying a direct-to-consumer cortisol panel.
- If you are stressed but otherwise well, start with sleep, exercise, nutrition, mental health support, and stress-management practices.
- If a product promises a “cortisol detox” or targeted belly-fat loss, treat that as a marketing claim, not a medical claim.
- If considering ashwagandha, discuss it with a clinician or pharmacist, especially if you are pregnant, breastfeeding, have liver or thyroid disease, or take regular medicines.
What We Still Do Not Know
We still do not know which stress-reduction programs meaningfully improve long-term metabolic outcomes through cortisol specifically. Many studies measure cortisol but not abdominal fat, and many measure stress or fat but not cortisol carefully.
We also need better long-term safety and effectiveness data for ashwagandha, including independent trials using standardised products, larger sample sizes, longer follow-up, active safety monitoring, and clearer reporting of conflicts of interest.
FAQ
Can stress cause belly fat?
Possibly, but not in the simple “high cortisol equals belly fat” way often claimed online. Chronic stress can influence appetite, sleep, activity, and cortisol biology. But human evidence is mixed, and cortisol is only one part of the picture.56
Should I test my cortisol because I have belly fat?
Usually no. Testing is most useful when a clinician suspects Cushing syndrome or another adrenal disorder. Random serum cortisol is not recommended as a screening test for Cushing syndrome.13
What symptoms make high cortisol more concerning?
Progressive central weight gain with easy bruising, wide purple stretch marks, muscle weakness, high blood pressure, diabetes, low bone density, facial rounding, or a fat pad at the upper back is more concerning than stress alone.414
Sources
- MedlinePlus. Cortisol Test. Updated 23 Dec 2024. Official source
- Bowles NP, Thosar SS, Butler MP, et al. The circadian system modulates the cortisol awakening response in humans. Frontiers in Neuroscience. 2022;16:995452. PMCID: PMC9669756. Human laboratory study
- El-Farhan N, Rees DA, Evans C. Measuring cortisol in serum, urine and saliva: are our assays good enough? Annals of Clinical Biochemistry. 2017;54(3):308–322. PMID: 28068807. DOI: 10.1177/0004563216687335. Review
- Cleveland Clinic. Cushing Syndrome: What It Is, Symptoms & Treatment. Updated 28 Jan 2026. Clinical source
- Lengton R, Schoenmakers M, Penninx BWJH, Boon MR, van Rossum EFC. Glucocorticoids and HPA axis regulation in the stress–obesity connection. Clinical Obesity. 2025;15(2):e12725. PMID: 39623561. DOI: 10.1111/cob.12725. Review
- Incollingo Rodriguez AC, Epel ES, White ML, Standen EC, Seckl JR, Tomiyama AJ. Hypothalamic-pituitary-adrenal axis dysregulation and cortisol activity in obesity: a systematic review. Psychoneuroendocrinology. 2015;62:301–318. PMID: 26356039. DOI: 10.1016/j.psyneuen.2015.08.014. Systematic review
- van der Valk ES, Savas M, van Rossum EFC. Stress and Obesity: Are There More Susceptible Individuals? Current Obesity Reports. 2018;7(2):193–203. PMCID: PMC5958156. DOI: 10.1007/s13679-018-0306-y. Review
- Rogerson O, Wilding S, Prudenzi A, O’Connor DB. Effectiveness of stress management interventions to change cortisol levels: a systematic review and meta-analysis. Psychoneuroendocrinology. 2024;159:106415. PMID: 37879237. DOI: 10.1016/j.psyneuen.2023.106415. Meta-analysis
- Li X, Xu Y, Li Y, et al. The Optimal Exercise Modality and Dose for Cortisol Reduction in Psychological Distress. Sports. 2025;13(12):415. PMID: 41441399. DOI: 10.3390/sports13120415. Network meta-analysis
- Albalawi AA. Dual impact of Ashwagandha: Significant cortisol reduction but no effects on perceived stress. Nutrition and Health. 2025;31(4):1395–1408. PMID: 40746175. DOI: 10.1177/02601060251363647. Meta-analysis
- NIH Office of Dietary Supplements. Ashwagandha: Is it helpful for stress, anxiety, or sleep? Updated 2 May 2025. Official source
- NCCIH and LiverTox. Ashwagandha: Usefulness and Safety; Ashwagandha – LiverTox. LiverTox updated 3 Dec 2024. Safety sources
- Nieman LK, Biller BMK, Findling JW, et al. The Diagnosis of Cushing’s Syndrome: An Endocrine Society Clinical Practice Guideline. Journal of Clinical Endocrinology & Metabolism. 2008;93(5):1526–1540. PMID: 18334580. DOI: 10.1210/jc.2008-0125. Guideline
- Savas M, Mehta S, Agrawal N, van Rossum EFC, Feelders RA. Approach to the Patient: Diagnosis of Cushing Syndrome. Journal of Clinical Endocrinology & Metabolism. 2022;107(11):3162–3174. DOI: 10.1210/clinem/dgac492. Clinical review